Heart failure prevention is not mysterious, and it is not a single decision. It is blood pressure control, glucose control, weight, movement and — for people who already have risk factors — two classes of drug that reduce the risk of developing it. Ranked by how much they move the needle, the list is short and unglamorous.
Medically reviewed by Dr. A. Collins, MDBoard Certified Internist · Updated 26 October 2026
What prevention actually means
Heart failure is a syndrome rather than a single disease: the heart cannot pump or fill adequately for the body’s needs. Two broad patterns matter for prevention. Reduced ejection fraction usually follows a heart attack or longstanding hypertension. Preserved ejection fraction is more often driven by age, obesity, diabetes and hypertension, and it is the pattern increasing fastest.
That distinction explains why prevention is mostly about metabolic health rather than cardiology heroics. The 2026 combined AHA/ACC/ADA/ASN guideline frames prevention explicitly around these shared risk factors (Ndumele, 2026).
The priority stack
These are ordered by the size of the effect and the strength of the evidence. The bars indicate relative impact, not a precise risk reduction you should expect personally.
Control blood pressure
The largest single lever. Pharmacological blood pressure lowering reduces cardiovascular events for both primary and secondary prevention across a wide range of starting pressures (BPLTTC, 2021). Treatment thresholds and targets are set out in the hypertension literature (Carey, 2022).
Treat diabetes early, and aggressively
Diabetes roughly doubles heart failure risk, and the modern approach treats glucose control as one component alongside renal and cardiovascular protection (Kalyani, 2025). The wider cluster is covered in cardiometabolic risk.
Lose weight if you carry excess
Obesity drives the preserved-ejection-fraction pattern through pressure, inflammation and direct myocardial effects. Weight reduction improves symptoms and physiology, and newer pharmacological options have changed what is achievable.
Move, including the small amounts
Non-occupational physical activity is associated with lower cardiovascular risk, and the association holds at volumes well below guideline targets (Garcia, 2023). Even weekend-only activity is associated with lower incident cardiovascular disease (Khurshid, 2023).
Use the drugs that prevent it, if indicated
SGLT2 inhibitors reduce heart failure hospitalisation and cardiovascular death in reduced-ejection-fraction heart failure (Zannad, 2020), with combination therapy studied further (Lin, 2022). This is a decision for a prescriber, not a lifestyle choice.
Limit alcohol and stop smoking
Alcohol is a direct myocardial toxin at sustained heavy intake, and smoking accelerates the vascular disease that precedes heart failure. Both are modifiable in a way that nothing else on this list is.
Blood pressure, in more detail
Because this is the top of the stack, it deserves specificity. The pooled trial evidence shows that lowering blood pressure reduces major cardiovascular events, and the relative benefit is broadly consistent across starting levels rather than confined to people with severe hypertension (BPLTTC, 2021).
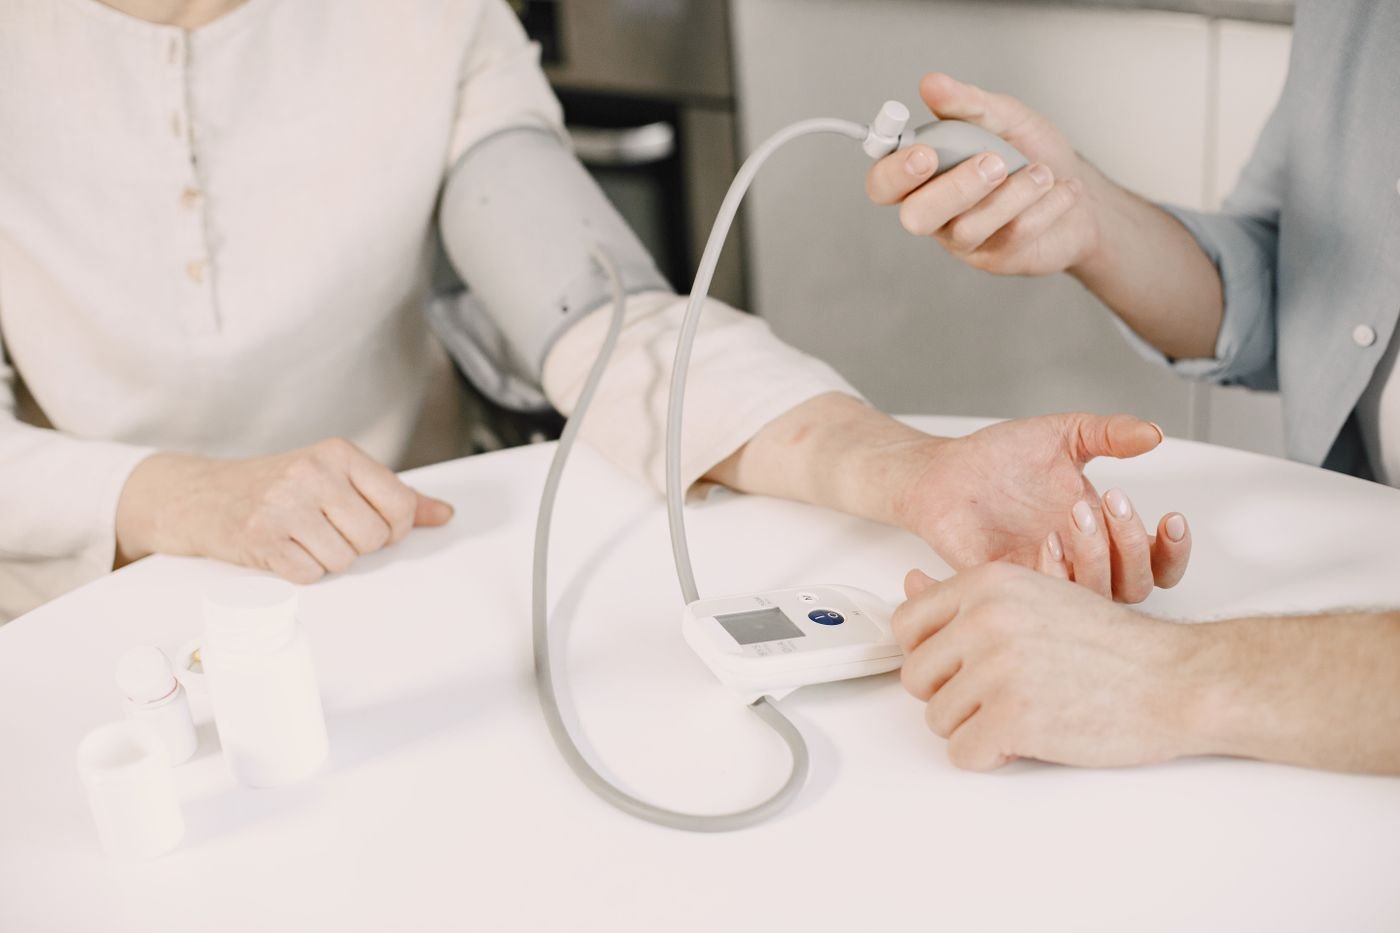
Practically that means three things: measure it properly rather than once in a clinic, treat it to target rather than accepting “a bit high”, and include sodium reduction and weight loss alongside medication rather than instead of it. The detail is in the high blood pressure guide.
Diabetes and weight
Diabetes is the risk factor where the modern therapeutic picture has changed most. Treatment now considers cardiovascular and renal outcomes rather than glucose alone (Kalyani, 2025), and the same drugs that protect the kidney and heart often help with weight.
- Get HbA1c measured if you have not had it done — undiagnosed diabetes is common and silent.
- Aim for remission-adjacent habits rather than perfection. Modest sustained weight loss changes the trajectory more than a dramatic short intervention.
- Ask about cardioprotective agents if you already have diabetes and another risk factor; that conversation is now standard rather than specialist.
- Watch the kidney numbers. Reduced kidney function amplifies cardiovascular risk, and the two are managed together — see the kidney diet guide.
The glucose mechanisms that drive this risk are set out in blood sugar dysregulation and hidden blood sugar spikes.
Movement: less is genuinely more than nothing
Cardiac rehabilitation improves outcomes in people who already have heart disease (Yamamoto, 2024), and the prevention data are consistent at much lower volumes. The reassuring finding is that the largest proportionate gain comes from moving from nothing to something.
That means walking, carrying shopping, stairs and gardening all count, and a single weekend session is not wasted. Starting points that do not require a gym are in at-home strength training and the best at-home routines.
What does not work
- Coenzyme Q10. Widely sold for heart failure, and a Cochrane review found it does not reduce mortality or improve ejection fraction meaningfully (Al Saadi, 2021).
- “Heart-healthy” supplements generally. The label is a marketing category, not an evidence category — see the immune supplement guide and the vitamins guide.
- Extreme salt restriction without guidance. Sodium reduction helps blood pressure, but very low intakes in people on diuretics need supervision rather than enthusiasm.
- Waiting for symptoms. Heart failure is easier to prevent than to treat, and the first symptom is often an admission.
A practical checklist
Five things worth doing this month, in order, with no equipment required.
- This week
Get your blood pressure measured properly
Two readings, seated, on two separate occasions. A single clinic reading is not a diagnosis.
- This week
Check HbA1c and kidney function
Both are standard blood tests and both change the plan if abnormal.
- This month
Set a sodium target you can actually hit
Under about 2 g of sodium a day. Most of it comes from packaged food, not the salt shaker.
- This month
Add two resistance sessions and daily walking
Strength protects function; walking protects the vasculature. Both scale down to ten minutes.
- Ongoing
Review medication with a clinician
Ask specifically whether any cardioprotective agent is indicated for you. That is a two-minute question with a large potential payoff.
The dietary side that supports all of this is covered in the heart-healthy food guide, the Mediterranean diet guide and anti-inflammatory foods. Warning signs are in heart disease warning signs, and sleep and weight interact with all of it — see improving sleep and how carbohydrates work.
If you want a structured place to start, checking your cardiovascular risk factors is a more useful first step than any supplement.
Some links in this article are affiliate links. If you buy through them we may earn a commission at no extra cost to you. This does not change the guidance above.
The numbers worth knowing
Prevention is easier to act on when the targets are concrete. These are the thresholds that matter, and the reason each one is on the list.
| Measure | Target | Why it matters |
|---|---|---|
| Blood pressure | Below 130/80 for most adults; individualised in frail older adults | The single largest modifiable driver of heart failure risk |
| HbA1c | Below 7% for most people with diabetes; individualised | Diabetes roughly doubles heart failure risk |
| Sodium | Under about 2 g of sodium a day | Lowers blood pressure and reduces fluid load |
| Body weight | 5-10% loss if carrying excess | Improves the obesity-related preserved-ejection-fraction pattern |
| Activity | 150 minutes a week moderate, or any meaningful increase from zero | The largest proportionate gain comes from the first increment |
| Alcohol | As low as practical; none is better | Alcohol is directly toxic to the myocardium at sustained intake |
| Kidney function | eGFR and urine albumin checked at least annually if at risk | Kidney and heart risk travel together and are treated together |
A single out-of-range number is information, not a verdict. What matters is the trend across two or three measurements, which is why the practical value of home blood pressure monitoring is so high.
Where prevention meets treatment
The boundary between preventing heart failure and treating it early has blurred, and that is a good thing. The same drugs that reduce events in established heart failure also reduce the risk of developing it in people with diabetes, kidney disease or established cardiovascular disease.
That means the conversation about prevention increasingly happens at the point where a risk factor is diagnosed, not when symptoms appear. If you have diabetes, hypertension with another risk factor, or known vascular disease, asking whether a cardioprotective agent is indicated is a reasonable and specific question.
- Ask about SGLT2 inhibitors if you have diabetes plus cardiovascular or kidney risk. The evidence in heart failure is strong.
- Ask about lipid management if you have established vascular disease, because the same plaque that causes heart attacks causes ischaemic cardiomyopathy.
- Ask what your actual numbers are rather than accepting “fine” as an answer. This is your data and you are entitled to it.
- Bring a list of everything you take, including supplements. Interactions are the most common avoidable problem at this stage.
None of this replaces the boring items at the top of the stack. A drug that reduces risk by a fifth does not compensate for untreated blood pressure, and the combination is what actually changes outcomes.
Common questions about preventing heart failure
Can heart failure be prevented?
Substantially, yes. Blood pressure control, glucose control, weight and activity reduce risk meaningfully. It cannot be reduced to zero, because age and genetics contribute.
What is the single most important thing?
Blood pressure. It is the largest modifiable driver, the evidence is strongest, and treatment is cheap and well established.
Do I need to worry if I have no symptoms?
Yes — that is exactly when prevention works. Hypertension and diabetes are silent for years, and the first heart failure symptom is often a hospital admission.
Is CoQ10 worth taking?
A Cochrane review found no meaningful benefit for mortality or ejection fraction. It is one of the more expensive ways to do nothing.
How much exercise is enough?
More than nothing, and the first increment matters most. Around 150 minutes a week of moderate activity is the guideline target, but the benefit curve starts well below it.
Are heart failure drugs only for people who already have it?
No. SGLT2 inhibitors in particular reduce heart failure events in people at risk, which is why the conversation now happens earlier. That decision belongs with a prescriber.
Sources
- Ndumele CE, et al. 2026 AHA/ACC/ADA/ASN guideline for the prevention, detection, evaluation and management of cardiovascular-kidney-metabolic syndrome. J Am Coll Cardiol. 2026. PMID 42265997
- Blood Pressure Lowering Treatment Trialists’ Collaboration. Pharmacological blood pressure lowering for primary and secondary prevention of cardiovascular disease. Lancet. 2021. PMID 33933205
- Carey RM, et al. Treatment of hypertension: a review. JAMA. 2022. PMID 36346411
- Kalyani RR, et al. Diagnosis and treatment of type 2 diabetes in adults: a review. JAMA. 2025. PMID 40549398
- Garcia L, et al. Non-occupational physical activity and risk of cardiovascular disease, cancer and mortality. Br J Sports Med. 2023. PMID 36854652
- Khurshid S, et al. Accelerometer-derived “weekend warrior” physical activity and incident cardiovascular disease. JAMA. 2023. PMID 37462704
- Zannad F, et al. SGLT2 inhibitors in patients with heart failure with reduced ejection fraction: a meta-analysis. Lancet. 2020. PMID 32877652
- Lin Y, et al. Efficacy and safety of combined SGLT2 inhibitor therapy. Front Cardiovasc Med. 2022. PMID 35665248
- Yamamoto S, et al. Impact of long-term exercise-based cardiac rehabilitation in patients with chronic heart failure. Circ J. 2024. PMID 38220206
- Al Saadi T, et al. Coenzyme Q10 for heart failure. Cochrane Database Syst Rev. 2021. PMID 35608922