


Some emulsifiers do change the gut microbiome and thin the protective mucus layer — in mice. In humans the picture is much earlier and messier than the headlines suggest, with one widely-feared emulsifier showing no measurable effect on permeability at all. Here is what the studies actually show, and what is worth changing on your shopping list.
What is the short answer?
Emulsifiers are ingredients that keep oil and water from separating. They are everywhere in processed food because they make products stable, creamy and shelf-tolerant. The concern is that some of them also interact with the gut’s bacterial community and the mucus layer that sits between that community and your immune system.
In mice, the effect is real and reproducible for two common emulsifiers in particular — carboxymethylcellulose (CMC) and polysorbate 80 (P80). They alter the microbiome composition, thin the colonic mucus layer, and increase markers of intestinal permeability.
In humans, one randomised controlled-feeding trial found that two weeks of CMC reduced microbial diversity and altered the gut metabolome, with some participants reporting gastrointestinal symptoms (Chassaing, 2022). That is a genuine finding. But it is one trial, in a controlled setting, at a dose chosen to test a hypothesis rather than to mirror a real diet.
What emulsifiers actually are
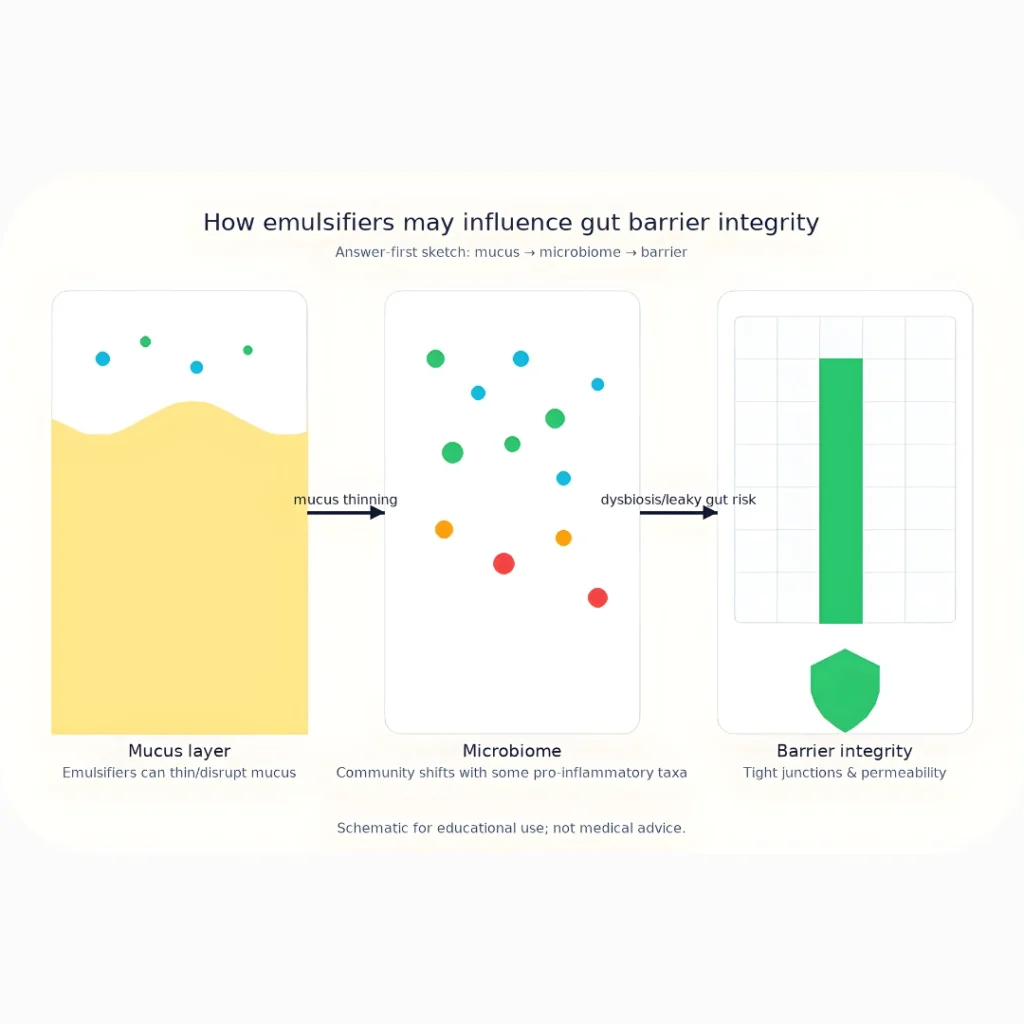
Chemically, an emulsifier has one end that likes water and one end that likes fat, which is why it can hold a mixture of both together. In food, that produces texture and stability. In the gut, the same property may let it interact with the mucus barrier, which is itself a lipid-rich structure.
The ones you will see on labels include:
- Carboxymethylcellulose (CMC) — E466, common in ice cream and plant milks
- Polysorbate 80 — E433, used in sauces and dairy alternatives
- Mono- and diglycerides — E471, extremely widespread
- Lecithin — E322, from soy or sunflower; the most benign of the group
- Carrageenan — E407, a seaweed-derived thickener with its own research literature
- Gellan and xanthan gum — fermentation-derived, generally well tolerated
That list matters because “emulsifier” is not one thing. Grouping lecithin with polysorbate 80 is like grouping olive oil with margarine because both are fats. The research concerns are attached to specific compounds, not the category.
What the animal studies showed
The mouse work is where this story starts, and it deserves to be described accurately rather than dismissed. Feeding mice CMC and P80 at doses within the range used in food production produced measurable changes: the composition of the microbiota shifted toward more pro-inflammatory taxa, the colonic mucus layer became thinner, and markers of bacterial translocation increased.
That combination is genuinely interesting because a thin mucus layer is one of the proposed routes by which gut bacteria get closer to the intestinal epithelium than they should. It is also a mechanism that has been explored in relation to metabolic and inflammatory disease.
What the human trials actually show
This is the part most articles skip. Here is the human evidence, study by study, with what each can and cannot tell you.
| Study | Design | What it found | Limitation |
|---|---|---|---|
| Chassaing, 2022 | Randomised controlled-feeding trial, CMC | Reduced microbial diversity, altered metabolome, some GI symptoms | Single compound, short duration, controlled dose |
| Wellens, 2026 | Placebo-controlled trial, five dietary emulsifiers | Effects on inflammation, permeability and microbiome measured across five agents | Recent; long-term clinical outcomes not yet available |
| Naimi, 2021 | Direct impact of common emulsifiers on human gut microbiota | Measurable shifts in microbiota composition and function | Ex vivo / short-term; not a clinical outcome |
| Metry, 2022 | Human intestinal permeability study, polysorbate 80 | No effect of P80 on intestinal drug permeability in humans | Permeability-specific endpoint, not microbiome |
Read together, these support a real but narrow conclusion: some emulsifiers measurably affect the human microbiome in controlled settings, and the downstream health consequences of that are not yet established. That is a meaningfully different claim from “emulsifiers are damaging your gut”.
Where the headlines overreach
Three specific overreaches are worth naming, because each one turns a preliminary finding into a lifestyle rule.
- Treating all emulsifiers as one. The evidence is strongest for CMC and P80. Lecithin, gellan and xanthan have little or no comparable signal, and lecithin is a normal component of eggs.
- Assuming animal doses translate. The mouse studies used defined doses in controlled diets. A human eating a varied diet is a different exposure entirely.
- Ignoring the null result. The polysorbate 80 permeability study found no effect in humans (Metry, 2022). That does not clear P80 of every concern, but any honest account has to include it.
There is also a structural problem with the way this research is reported. Most of the alarming claims trace back to a small number of animal studies, restated as human findings. The stronger and less exciting evidence is about ultra-processed food as a category, which is where the next section goes.
The bigger picture: ultra-processed food
If you want a claim with real epidemiological weight behind it, it is this one. An umbrella review of meta-analyses on ultra-processed food exposure found associations with a wide range of adverse health outcomes, across many studies and populations (Lane, 2024).
A major review of ultra-processed foods and food additives in gut health reached a careful conclusion: the evidence for harm from UPF as a category is more consistent than the evidence for any specific additive, and disentangling the two is genuinely difficult because additives travel with the foods that contain them (Whelan, 2024). Reviews of the additive-microbiota literature reach similar positions — effects are demonstrable, clinical significance is not settled (Zhou, 2023), (Bevilacqua, 2024).
This is the same problem that shows up in the seed oils debate and in artificial sweeteners: a single ingredient gets blamed for the effect of the food matrix it arrives in.
Reading labels without becoming obsessive
If you do want to reduce intake, the practical targets are the products where emulsifiers are doing heavy structural work — because those are also the most processed items.
| Product | Common emulsifiers | Simpler swap |
|---|---|---|
| Plant milks | Gellan gum, CMC, lecithin | Unsweetened varieties with fewer additives, or make your own |
| Ice cream | Mono- and diglycerides, carrageenan, guar | Buy less often; choose shorter ingredient lists |
| Creamy dressings | Xanthan, polysorbate 80 | Oil and vinegar, made in ten seconds |
| Packaged baked goods | Datem, mono- and diglycerides | Bread with flour, water, salt, yeast |
| Protein powders | Lecithin, xanthan | Compare labels; lecithin is the least concerning |
Two caveats about label-reading. First, a shorter ingredient list is a decent proxy for less processing, but it is not a guarantee of anything. Second, “clean label” is a marketing category, not a regulatory one — the same trap covered in foods that seem healthy but are not and in the toothpaste marketing problem.
If you are choosing a plant milk specifically, the additive load varies enormously between brands. Some unsweetened options are essentially nuts and water; others are a chemistry set. Comparing two cartons is genuinely informative:
- Organic unsweetened almond milk — check the gum content on the label
- Almond protein powder — protein products often carry lecithin, which is the benign end of the category
- Organic oat milk — oat drinks frequently contain added gums and oils
AllAboutHealthToday may receive a commission at no additional cost to you.



What a realistic reduction looks like
Most people who decide to cut emulsifiers do it in the wrong order. They start with the hardest thing — giving up a favourite product entirely — and quit within a fortnight. The versions that actually hold are unglamorous and partial.
- Start with the highest-frequency item. If you have plant milk in coffee twice a day, that is 700 exposures a year from one product. Changing it beats eliminating something you eat monthly.
- Change one category at a time. Milk alternatives, then dressings, then baked goods. Sequential changes are evaluable; simultaneous ones are not.
- Do not replace additives with “clean label” products. That term is unregulated, and the substitution often costs more for no measurable difference.
- Keep a symptom log if you have gut symptoms. Four weeks, one change, written down. Without a record you will attribute improvement to whatever you changed most recently.
- Accept that lecithin is not the enemy. If your only emulsifier is soy lecithin in dark chocolate, the expected benefit of eliminating it is close to zero.
There is a behavioural reason for this approach. Research on dietary change consistently finds that restriction without substitution fails, and that the most durable changes reduce frequency rather than eliminate categories. The same pattern shows up in the additive literature: the population-level signal is about dietary pattern, not about any single ingredient appearing or disappearing from a label.
What would change my mind
It is worth being explicit about what evidence would move this from “early and uncertain” to “avoid”. A randomised trial with clinical endpoints — not microbiome composition, but measured disease outcomes — over a meaningful duration, at real-world doses, would do it. So would consistent replication of the CMC findings across several independent groups using different designs.
What would not change my mind: another mouse study, another cross-sectional correlation between ultra-processed food and a health outcome, or a headline that reports a microbiome shift as if it were a disease. The gap between “changes your bacteria” and “makes you ill” is where most of this literature currently sits.
Who should actually care
Not everyone needs to change anything, and the honest triage looks like this:
- If you have IBS or IBD: reducing emulsifiers is a reasonable, low-risk experiment. The mechanistic story is most plausible in people whose gut barrier and microbiome are already compromised.
- If you have a sensitive gut but no diagnosis: try a four-week reduction before assuming anything. If nothing changes, you have your answer.
- If you eat a largely whole-food diet: your emulsifier intake is already low. Optimising further has negligible expected benefit.
- If ultra-processed food is most of your intake: the emulsifiers are not the main problem — the overall pattern is. Fix the pattern.
The gut side connects to more than digestion. The microbiome’s relationship with mood and cognition is covered in the gut-brain connection, fermented foods have their own evidence base in the fermented foods guide, and the leaky-gut framing is examined in leaky gut explained. If you have specific bacterial overgrowth symptoms, SIBO is the more relevant starting point than additives.
Common questions about emulsifiers
Should I avoid all emulsifiers?
No. The category includes compounds with no meaningful evidence of harm, like lecithin, alongside the two with the strongest signals, CMC and polysorbate 80. Blanket avoidance is not supported by the human data and would eliminate a lot of foods for no measurable benefit.
Is carrageenan bad for you?
It has its own research literature and has been argued about for decades. The human evidence for harm at typical food levels is not established, but if you have active inflammatory bowel disease it is one of the additives people commonly trial removing. That is a reasonable personal experiment, not a general rule.
Are natural emulsifiers like lecithin safer?
Generally yes, in the sense that there is far less evidence of any gut effect. Lecithin is a normal constituent of egg yolk and soy, and it appears in the diet regardless of processed food intake.
Do emulsifiers cause inflammation?
In mice, some do, through effects on the mucus layer and microbiome. In humans, the evidence shows microbiome shifts and is still short of demonstrating clinical inflammation at normal intakes. “Associated with” and “causes” are doing very different work in the headlines.
Does cutting emulsifiers help IBS?
For some people, plausibly. The mechanistic rationale is strongest in people with an already-compromised barrier. The sensible approach is a defined trial period with a symptom log, rather than an indefinite restriction you cannot evaluate.
What about xanthan gum and gellan gum?
These are fermentation-derived and generally well tolerated at food levels. They appear in the plant milks and dressings you might swap to, which is a useful reminder that “fewer additives” and “no additives” are not the same goal.
Sources
- Chassaing B, et al. Randomised controlled-feeding study of dietary emulsifier carboxymethylcellulose reveals detrimental impacts on the gut microbiota and metabolome. Gastroenterology. 2022. PMID 34774538
- Naimi S, et al. Direct impact of commonly used dietary emulsifiers on human gut microbiota. Microbiome. 2021. PMID 33752754
- Wellens J, et al. Effect of five dietary emulsifiers on inflammation, permeability and the gut microbiome: placebo-controlled trial. Clin Gastroenterol Hepatol. 2026. PMID 40816342
- Metry M, et al. Lack of an effect of polysorbate 80 on intestinal drug permeability in humans. Pharm Res. 2022. PMID 35672541
- Whelan K, et al. Ultra-processed foods and food additives in gut health and disease. Nat Rev Gastroenterol Hepatol. 2024. PMID 38388570
- Lane MM, et al. Ultra-processed food exposure and adverse health outcomes: umbrella review of epidemiological meta-analyses. BMJ. 2024. PMID 38418082
- Zhou X, et al. The impact of food additives on the abundance and composition of gut microbiota. Molecules. 2023. PMID 36677689
- Bevilacqua A, et al. Ultra-processed food and gut microbiota: do additives affect eubiosis? Nutrients. 2024. PMID 39796436


